Managing your Diabetes during the holiday season

By Janet Crain, RN, Wesley Nurse

November is American Diabetes Month® and the beginning of the holiday season! As hard as you've worked to stay on course with managing your diabetes throughout the year, the holiday season has the potential to throw you off. Travel, parties, big meals, snack foods at the office and drinking all create a challenging environment for eating healthy. Add to that the days of travel with little scheduled exercise, and it becomes a real effort to stay on track. "How can I eat healthy during the holidays?" It's one of the most common questions asked by people with diabetes—or anyone who's made a commitment to eating with their health in mind.

If you follow these strategies, you can maintain your blood sugar levels and enjoy the parties and gatherings along with everyone else. However, just like everything else with diabetes, you have to take a few extra steps:

  • Eat breakfast or snacks earlier in the day and avoid the idea of sav­ing carbs for the big feast later on. Eat a small, balanced meal before you leave home to avoid overindulging. If you skip meals, it may be harder to manage your blood sugar.
  • Limit the number of serv­ings of starchy foods on your plate. It might be tempting to have some mashed potatoes, sweet potato casserole and rolls; however, try to choose just one of these items. If you have a sweet treat, cut back on other carbohydrates (like potatoes and bread) during the meal.
  • Choose vegetables first and choose fruits and vegetables served raw, grilled or steamed. Avoid vegetables in creams, gravies and butter.
  • Stick to calorie-free drinks such as water, tea, selt­zer or diet sodas instead of punch or mixed drinks. Sip a large glass of water or mineral water to keep you hydrated and provide you with a better option than alcohol.
  • If you choose to drink alcohol, limit the amount and have it with food. Talk with your health care team about whether alcohol is safe for you. Women should drink no more than one alcoholic beverage a day and men should drink no more than two.
  • Enjoy your favorite holi­day treats, but take small portions, eat slowly and savor the taste and texture. Offer to bring a healthy dish along to the party so that you will have more healthy food choices.
  • Try not to hang out near the food to avoid grazing. Find a comfortable spot across the room and focus on socializing instead of eating.
  • After your meal, take a walk with family and friends. Exercise will also get you moving, keep you focused on your goals, and give you a welcome break from being surrounded by treats. Exercise is also a great way to lower blood sugar levels.
  • If you overindulge, don't beat yourself up. If you eat more carbs or food than you planned for, don't think you have failed, just make a plan to get back on track.
  • If you go out more often and stay out later during the holidays, you're likely to get less sleep. Sleep loss can make it harder to control your blood sugar. Also, when you're sleep deprived you'll tend to eat more and prefer high-fat, high-sugar food. Aim for 7 to 8 hours per night to guard against mindless eating.

Most of all, remember what the season is about—celebrating and connecting with the people you care about. When you focus more on the fun, you won't focus as much on the food!

Learn more by visiting the following websites:
https://www.diabeteseducator.org/docs/default-source/legacy-docs/_resources/pdf/general/AADE_Holiday_toolkit.pdf 
http://www.cdc.gov/features/diabetesmanagement/ 

Janet Crain, RN, is a Wesley Nurse with Methodist Healthcare Ministries of South Texas, Inc. Methodist Healthcare Ministries' Wesley Nurse program is a faith-based, holistic health and wellness program committed to serving the least served through education, health promotion and collaboration with individual and community in achieving improved wellness through self-empowerment. Learn more at www.mhm.org. 

Listening to patients to make a difference

By Carol Chavez, regionalization & partnership specialist

On my first day as a regionalization & partnership specialist for Methodist Healthcare Ministries, I hit the ground running and traveled to Brownsville, Texas, on a Sunday afternoon to attend our Sí Texas Project Convening and Evaluation Learning Collaborative sessions. Throughout the four-hour drive, I kept mentally going over potential topics of conversation. I was excited to meet our funded partners and start developing a rapport. I took that first opportunity to network with key individuals and began building relationships with sub-grantees, executive directors and other associates from partner nonprofits. Nearly a year later that continues to be the foundation of my role: forming long-lasting, valuable and trustworthy relationships with our funded partners and with community members in our 74-county service area in South Texas.

Part of my job is to also assist in managing Methodist Healthcare Ministries' Eugene Washington Patient-Centered Outcomes Research Institute (PCORI) award. The community engagement five-part series titled, Advancing Health in South Texas, aims to gather patients and key stakeholders across a 20-county area to develop a coordinated regional approach for patient-centered research and evaluation among university systems, academic institutions, managed care organizations and public health systems. The objective is to learn about patients' perspectives and important health issues in their communities to better frame conversations with stakeholders.

A month into my position, in early February 2016, I coordinated the first PCORI Engagement Series Session: What Matters to You? Methodist Healthcare Ministries, along with our partner Health Resources in Action (HRiA), hosted six, two-hour focus groups in Cameron, Hidalgo, Jim Wells, Nueces, Webb and Zavala counties. I called this trip the "South Texas county tour." Our ambitious goal was to complete all six focus groups in three days.

Hearing firsthand from community members was a great learning opportunity. I learned that wait times to see a doctor ranged from one month to six months. Some patients shared that after hours of waiting for a doctor they'd be called in only to be left confused and frustrated because the doctor didn't speak the same language. Patients expressed that they did not have a trusting relationship with their providers. It was heartbreaking to also learn that critical prenatal care was not easily accessible.

Many communities both in the Rio Grande Valley and Coastal Bend areas have a great need for Methodist Healthcare Ministries' services – to facilitate health care access, to convene key stakeholders, and to connect communities with local not-for-profits and health care providers. Being part of Methodist Healthcare Ministries' community engagement work allows me to be an advocate and bring community voices to the forefront. It enables me to be part of the conversation of health inequalities so I can work on solutions for better health services in rural areas. I believe Methodist Healthcare Ministries is creating a significant platform by bringing down communication barriers between patients and system level stakeholders so that together they can discuss opportunities to increase access and improve health.

In my new role I have a new lens and I can see our organization is on the path to implementing groundbreaking initiatives between health care systems and regional communities to impact many lives. By continuing to connect with communities, we truly bring our organizational mission into action: Serving Humanity to Honor God by improving the physical, mental and spiritual health of those least served.

Funded partner spotlight: Community Health Centers of South Central Texas, Inc.

Methodist Healthcare Ministries of South Texas, Inc. invests in organizations that demonstrate a commitment to meeting an unmet health care need in the community. When we award grants, we look for organizations with a history of providing community-based health care, patient-centered models and that are effectively addressing the social determinants of health. We are committed to having a measurable, systemic impact at the community and regional level, and holding ourselves accountable for these results.

We lovingly refer to grantees as funded partners as this partnership serves as an extension to Methodist Healthcare Ministries' programs and services and reach into the community.

This month we're profiling Community Health Centers of South Central Texas, Inc. (CHCSCT), a nonprofit health care provider. Methodist Healthcare Ministries has partnered with CHCSCT since 1994.

CHCSCT has been providing health services to the people of Gonzales County since 1966. In the time since, it has grown to seven clinic locations in Bastrop, Elgin, Gonzales, Lockhart, Luling, Seguin and Victoria counties. CHCSCT's service area has been designated as a Medically Underserved Area meaning there is a health professional shortage and medically underserved population present. CHCSCT offers unconventional hours at each clinic to meet the needs of their population.

CHCSCT operates with a patient-centered philosophy; primary care is comprehensive, team-based, coordinated, and accessible and focused on quality and safety. The Center has received accreditation through Joint Commission and as a Patient Centered Medical Home.

To date, Methodist Healthcare Ministries has awarded CHCSCT $2,155,183. Grants have supported:

  • Dental provider to continue serving people in the rural community who otherwise would not be able to afford oral health care. The dental provider in rural Gonzales recently earned recognition as the "Best Dentist" in Gonzales. This program has been funded since 2004.
  • Integrated behavioral health navigators serve as the link to integrated care. An important link to integrating behavioral health services with primary care is the Behavioral Health Consultant (BHC). CHCSCT and Bluebonnet Trails Community Services (BTCS), the local mental health authority, in 2009 realized that they were two organizations with a similar mission. Together, they began working as one to serve the communities they shared. The behavioral health consultant is one of the outcomes of a relationship positively affecting access to high quality integrated services. The BHC links patients referred by the local mental health authority to CHCSCT – a federally qualified health center – or when there is a need CHCSCT to BTCS. The BHC is an integral part of the integrated treatment team who assists the patient in navigating through both systems and connecting staff of both organizations. The patient receives primary medical, dental or behavioral health services during the visit without delay versus being referred for services. This program has been funded since 2015.
  • Women's health in rural communities. Studies have shown female residents in rural areas do not routinely seek or receive well woman care; thus, are less likely to obtain screenings for cervical cancer. This health issue particularly affects the Hispanic population. Many report fear as the cause, as a diagnosis could implicate many hardships including surgery, stripping them of their female identity. The program goal is to improve the screening rate through the use of patient navigators at each clinic site to educate female residents and connect them to well-women resources with a licensed vocational nurse educating participants on proactive prevention strategies. This program has been funded since 2015.

"The funding from Methodist Healthcare Ministries has been a blessing allowing CHCSCT to be creative in moving from a treatment model of services to a preventive model of services. We have been able to keep a valuable provider, increase access to care and focus on increasing screenings to women of the communities we serve," explains Henry Salas the CEO of Community Health Centers of South Central Texas.

To learn more about CHCSCT, visit www.chcsct.com. To learn more about grant-making at Methodist Healthcare Ministries, visit www.mhm.org/about/grantmaking. 

Funded Partner Spotlight: Hill Country Daily Bread Ministries, addressing rural poverty through relational ministry

By Jane Hevezi, grants specialist

I am in a unique position to intimately see how Methodist Healthcare Ministries' funding to nonprofit organizations serves as an extension to the organization's mission of creating access to health care in South Texas. We recently had the privilege of sitting down with one such organization. Hill Country Daily Bread Ministries, a regional resource center located in Boerne, Texas, has been helping transform the lives of their neighbors in poverty for the past 16 years.

In 2016, Methodist Healthcare Ministries awarded nearly $83,000 to Hill Country Daily Bread Ministries to support their Family Mentoring Resource Program, a program impacting the lives of underserved individuals and families in the Texas Hill Country. Elements of the program include employment assistance, family and social support, longitudinal case management and mentorship, and resources intended to alleviate situational and generational poverty.

"This is the brainchild of my husband, David. We started in a garage 16 years ago. We had this blueprint of relational ministry from the very start. We knew poverty wasn't going to be solved by material things. We had to blend it with a relationship with Christ. Just seeing how God has blessed us over the years and brought wonderful partners like Methodist Healthcare Ministries to help us fulfill that dream – it can be pretty overwhelming at times," explains Agnes Hubbard, co-founder and executive director at Hill Country Daily Bread Ministries.

"What a joyful thing it is to look around and see people walk in the door with their head held low and hanging, sometimes in tears, and about an hour later after working with a case manager, walking upright with a smile on their face, there's just nothing like that. They know people love them here. That's transforming for both client and us."

Learn more about grant-making at Methodist Healthcare Ministries. To learn more about Hill Country Daily Bread Ministries, visit www.hillcountrydailybread.com. 

A small change can make a big difference

By Deborah Laurents, Wesley Nurse in Elgin, Texas

A gentleman I know, Greg Silkenson, has a ministry called "Church on the Street." Greg goes to Veteran's Park almost every Friday and provides breakfast tacos, coffee and juice to anyone who shows up. The ministry usually serves the men who wait there for someone to give them a job. Greg is very faithful, caring and compassionate and has built strong relationships.

A few weeks ago, I visited with Greg and the men there. Greg introduced me to Mr. J, a gentleman who receives life-saving health care treatments three days a week in Austin.

Mr. J told me his treatments were Tuesdays, Thursdays and Saturdays. Mr. J. said he rides the bus for $7.00 round trip on Tuesdays and Thursdays, but on Saturdays, the bus does not provide transportation. In order to make it to his appointments, he has to pay someone $50.00 to take him.

With Mr. J's permission, I called his case manager and asked if Mr. J's treatment days could be changed to Mondays, Wednesdays and Fridays. I pointed out the financial hardship it was causing. I was told it was unlikely his schedule could be changed.

As a Wesley Nurse, I help community members obtain access to resources. I felt I couldn't give up. I had to help. God and persistence won. The third time I called, the regular case manager was not there and another case manager returned my call. When I explained to him the hardship Mr. J. was having, the case manager immediately said, "Traveling from Elgin gives him priority in getting his schedule changed. I will see what we can do."

Shortly afterwards, I stopped by to let Mr. J. know about the conversation. I was very happy to learn his schedule had been changed. With a big smile, Mr. J. said "thank you."

Deborah Laurents, RN, is a Wesley Nurse with Methodist Healthcare Ministries of South Texas, Inc. Methodist Healthcare Ministries' Wesley Nurse program is a faith-based, holistic health and wellness program committed to serving the least served through education, health promotion and collaboration with individual and community in achieving improved wellness through self-empowerment. Learn more at http://www.mhm.org/programs/health-ministries. 

Moving Upstream: Health starts outside of the doctor’s office

By Edlín Maldonado-Fuller, collaborative grants specialist

The United States leads the world in medical research and medical care. This would make you believe we are the healthiest people on Earth. Surprisingly, however, the U.S. isn’t even in the top 25 countries on some of the most important health indicators, like how long we live. We’re behind Bosnia and Jordan! We have the most expensive health care system in the world, yet rate 33rd in quality of care (read more). The majority of our health care costs go to direct care to manage the “downstream” consequences. Not much is invested in the “upstream” factors like housing, education and employment. Yet, years of research tell us good health depends on many things beyond health care.

Our ZIP code is a strong predictor of how long we live and of our quality of life. Health care (clinical care) is not the only aspect that determines our health and is not the sole answer to better health. Nonmedical factors play a substantially larger role (read more). Even if every individual in Methodist Healthcare Ministries’ 74-county service area in South Texas could afford to see a doctor when they were sick, it would not necessarily result in healthier communities. If we look closer, we learn that various factors within our communities truly influence both our health and our ability to make healthier choices.

Health starts outside of the doctor’s office – in our homes, workplaces, schools and places of worship. We need to enable people to choose the best path to health and ensure that everyone has the tools and resources to make healthy decisions. As a health care system, I believe we should seek upstream solutions to drive vast improvements in health. We should consider promoting health as a community, and unite health and other sectors and disciplines. We need to focus on the nonmedical determinants of health present in our communities, such as social, environmental and behavioral factors.

As an organization, we acknowledge achieving healthy communities takes different, localized approaches. The needs and resources of urban areas vary from rural areas. And not all rural areas face the same challenges. How we work together with communities is changing and is moving toward intentional partnerships to address the Social Determinants of Health (read more). Thankfully, various interventions exist to help our health care system address the nonmedical factors, both within the system and externally.

Still, how do we best address the other factors beyond clinical care that greatly impact our health? Methodist Healthcare Ministries is hard at work meeting with partners across the Rio Grande Valley and greater Coastal Bend regions to understand the needs and resources of communities. We ask questions and listen attentively to identify opportunities for collaboration, alignment, and new ways to leverage resources. Guided by our community partners, we seek to build cross-sector partnerships and promote health. We are also committed to identifying different ways to collect and use determinants of health data to inform and create transformational change.

God intertwines our talents with the needs of others to allow us the privilege of touching, serving, and inspiring others as they journey to become healthier communities. Imagine what could happen if we focused our efforts on preventive measures and upstream factors to keep people healthy!

Edlín Maldonado-Fuller is the Collaborative Grants Specialist for Methodist Healthcare Ministries. She provides technical assistance to community partners in Methodist Healthcare Ministries' service regions, ranging from grant-writing, vetting grant opportunities, supporting collaborative funding initiatives and sharing information about development resources.

Learning about the body in a Bible study

By Donnelle Storrs, Wesley Nurse

As a faith community nurse, I strive to provide compassionate care and consider the spiritual needs of patients while addressing their physical health. I attend Bible studies to meditate on the scriptures, and listen and learn about the Lord without really thinking about the physical body. How amazing is it then to go to a Bible study and have the Lord open my eyes to things I had not seen before?

John 9 tells, in my mind, a beautiful story to read. In summary, Jesus and his disciples happen upon a man blind from birth – for ease of reading, we'll call the blind man Bubba. After a short discussion, Jesus spits into the dirt to create mud. He places the mud over Bubba's eyes and instructs him to go wash in the pool of Siloam. Bubba follows Jesus' instructions and is healed.

Bubba tells his experience to the Pharisees who are incredulous. They ask for Bubba's parents to give testimony, not believing that he was truly blind before meeting Jesus. The parents confirm his identity and that he had been born blind, however, they deny any knowledge of Bubba being healed. The parents remind the Pharisees that Bubba is of age to answer the questions so the Pharisees ask again how he was healed. At this point, Bubba has questions of his own. "I already told you, and you didn't listen. Why do you want to hear it again?" (CEB Jn 9:27a) Bubba is then expelled from the group.

Jesus returns, and as he reveals himself to be the son of God, Bubba believes and worships him. "Jesus said, 'I have come into the world to exercise judgment so that those who don't see can see and those who see will become blind.'" (CEB Jn 9:39)

The chapter before Bubba's story, in the Temple, "Jesus spoke to the people again, saying, 'I am the light of the world. Whoever follows me won't walk in darkness but will have the light of life.'" (CEB Jn 8:12)

When preparing a health education program on eyes and vision, I was captivated by a simple truth: in order to see, there must be light. Of course, it makes perfect sense—we are unable to see in pitch black darkness. There must be light in order for our eyes to be able to work. But take a moment to reflect on John 8:12 along with what is physically required for vision—Jesus is the light of the world; there must be light in order to see. I paused. It seemed so simple. We may live in these physical bodies, but do we truly see if we have not encountered Jesus?

There is a saying from Matthew 6:22 (CEB) that says, "The eye is the lamp of the body. Therefore, if your eye is healthy, your whole body will be full of light." Did you know that an eye exam could tell you how you're doing with your blood pressure? This same exam can tell you if your diabetes is under control? It's true. The eye is the only place where a doctor can view a vein, artery and nerve without any incision. The eyes are great indicators of health, which is why regular eye exams (yearly) are so important. It's not just your eyes being checked, but also how your heart is working and your blood is flowing.

I had studied eyes and vision in nursing school and read articles since then on the topic. I had seen these verses from John 8 and 9; I had just never really thought of them together. We are beautifully and wonderfully made. In seeing these concepts together, I realized that the Lord could teach me about my body in a Bible study as well as in a nursing class.

Stay tuned! I hope to share with you more about how health and Bible classes work cohesively.

Donnelle Storrs, RN is a Wesley Nurse at Methodist Healthcare Ministries of South Texas, Inc. Methodist Healthcare Ministries' Wesley Nurse program is a faith-based, holistic health and wellness program committed to serving the least-served through education, health promotion and collaboration with individuals and communities to achieve improved wellness through self-empowerment. Learn more at www.mhm.org/programs/health-ministries. 

Banding together for the greater good: Premont’s successful community effort

By Abel Garcia, research & community impact analyst

I grew up in the Coastal Bend region of Texas in a small town called Premont, about 30 miles south of Alice. Not long after graduating high school, I left town for college and I haven't lived there since. Although I've been gone for over 20 years, I still consider Premont my home. I still have a lot of family there including my father, sister, nieces and a whole bunch of primos, tías and tíos. A handful of friends I went to school with still reside there as well. The city of Premont has a great deal of needs, and since graduating with a Masters in Social Work, I've often been conflicted about living so far away and not directly giving back to my community. Growing up in Premont shaped me as a person; it influenced why I became a social worker. Working at Methodist Healthcare Ministries has helped ease that inner conflict. The work I've been doing to support regionalization efforts in the Coastal Bend will ultimately impact my hometown in a positive way.

Premont, like many rural communities in the Coastal Bend, faces many challenges associated with the Social Determinants of Health — factors beyond clinical care that impact health such as education, diet and exercise, access to care, community safety, and family and social support to name a few. If improved, these factors can help make communities healthier places to live, learn, work and play. Some of Premont's challenges include a high rate of poverty, low education attainment, limited access to health care, limited access to healthy food, and high numbers of obesity and diabetes. A good portion of what I do with Methodist Healthcare Ministries is gathering this type of public health information to help inform others of the work that we conduct in the area.

A few months ago I attended the 2016 Summer in the Park Festival hosted by the Premont P.R.I.D.E. (Premont Residents Involved in Dynamic Education) Foundation. The P.R.I.D.E. Foundation started in 2012 after the Texas Education Agency (TEA) had taken a rare action to revoke the local school district's accreditation. Premont ISD had been ordered to close down the summer of 2012. TEA decided to take this action after years of unacceptable academic ratings, complaints about rat and mold infested facilities, allegations of dysfunctional school leadership and constant budget deficits. The TEA has only shut down five schools since 1999, and in each case the decision was final, but Premont ISD leadership took advantage of an option to appeal. Knowing that losing the school district would be devastating to the community, the community worked together by raising funds and volunteering their time to repair and rebuild some of the rundown facilities. The community worked with school district leaders and developed strategies to improve attendance and test scores. The school district even cut their football program; which if you're familiar with small Texas towns is a big sacrifice. The community worked to form a partnership between Premont ISD and Texas A&M University-Kingsville to improve academics. All this work resulted in the school district receiving a reprieve from the TEA. The P.R.I.D.E. Foundation was formed as a result of the community's struggle to organize and garner support to save the school district, and in turn became an ongoing advocate for dynamic and quality education for the children of Premont.

Summer in the Park is the P.R.I.D.E. Foundation's big annual fundraiser. This year, Methodist Healthcare Ministries proudly sponsored the event in part. Initially, it started out as a call out to all Premont ISD alumni to come support the community during the TEA crisis. Now it's grown into a full-fledged community festival with food, music, games, a 5K run/walk, and a 3-on-3 basketball tournament. Proceeds go toward the school district. Organizers of the festival pride themselves in saying that the event serves as a symbol of community. They feel it serves as a way for Premont's children to form strong associations with what it is like to live in a small town with limited resources, and that sometimes in order to make a difference, you have to sacrifice your personal needs for what is best for everyone else.

I attended this year's Summer in the Park event with my father and had a great time. It was unseasonably cool for late June so the turnout was excellent. While reconnecting with friends and family, I was asked numerous times about where I live and where I work. When I told folks I worked for a not-for-profit in the health care industry, the conversation naturally steered toward health. Nearly everyone I spoke to recounted their struggles with diabetes, obesity, high blood pressure, the cost of medicine, and not being able to see a doctor because there isn't one nearby (which is one of my 76-year-old father's primary complaints, along with being too old to sit and wait all day to see a doctor). "Why go?" he often says jokingly, but I know it is a source of frustration for him and many others in the community. In order for my dad to see a primary care doctor, he has to travel more than 30 miles to Alice or Kingsville. Often times he gets to his appointment on time, but still ends up sitting in a packed waiting room for hours and is sometimes asked to come back another day. His only other options are to use one of the local emergency rooms or travel another 40 miles or so to Corpus Christi to see a primary care doctor. Even though my dad is fully insured with Medicare and has transportation, seeing a doctor is hard work.

Unfortunately, I think there's a misconception that small towns are filled with people who don't care about their own health, and that the community is the reason the county ranks so poorly when it comes to health outcomes. I think this interpretation is flawed and ultimately detrimental to the health of communities like Premont. While visiting Premont I witnessed a community that is vibrant, strong, and prideful in their ties with one another. I saw individuals eager to learn better ways to manage their health but overburdened by the huge hurdles they need to cross just to see a primary care physician or get their medicine.

There is evidence that small communities like Premont indicate a strong awareness about health. Evidence like the 5K run/walk that was added to Summer in the Park after its second year. The event was proposed by a few community members who had made personal commitments to live healthier lifestyles. This year, more than 50 people participated in the 5K, with an 11-year-old as the youngest participant and an 82-year-old as the oldest. Evidence like the 3-on-3 basketball tournament that has taken place since the first festival. Participants practiced for weeks at their homes and at the local community gymnasium. Children and adults for generations have packed the "old gym," a 1950s era gymnasium owned by the city, to be active and play. My mother taught my brother and me how to shoot free throws at that gym.

A community that bands together to save their school district from what the TEA even thought was a lost cause, is a community that is resilient and cares about its overall well-being. If we look closely, outside of the numbers and metrics, I think we can find a great deal of passion and community commitment for health care in rural communities. As Methodist Healthcare Ministries moves forward with regionalization efforts, I believe rural communities like Premont can be impacted in a profoundly positive way. When communities are given the opportunity and resources to build on their strengths, change can happen for the better. As Methodist Healthcare Ministries connects with local leaders and listens to community needs, not only will health be impacted, but people's perceptions of what is possible will too.

Mobile dental clinic travels to Brady to deliver much needed care

Methodist Healthcare Ministries Wesley Nurses recently participated in Texas Mission of Mercy – a mobile dental clinic that travels around the state providing basic dental care (including cleanings, fillings, or extractions), free of charge, to uninsured Texans. They provide services without any pre-qualifications; therefore, patients do not have to prove their poverty or residency. The event was held at Brady High School in Brady, Texas, and brought much-needed oral health care to the area. Volunteer dentists (assisted by volunteer dental students, hygienists, and dental assistants) examined and treated 238 patients in attendance.

Three Wesley Nurses – Theresa Whitley (Mertzon), Theresa Standage (Kerrville) and Charlotte Johnson (Brady) – served alongside the more than 200 volunteers by registering clients and assisting them with their health assessments.

"I am so proud to have been part of this service, especially after listening to patients express how happy they were to be able to smile and show their teeth and to have rotted teeth removed," said Johnson. "One man told me his mouth had never felt so clean."

Patients were lined up at the door at 5:30 a.m. Some slept in front of the school because they didn't want to miss the opportunity to be seen. Some drove all night to get to the event because this was their only opportunity to get dental care. Most patients were local, but some came from as far as Austin, Houston, Beaumont, and Fredericksburg. Texas Mission of Mercy provided help to people with dental problems, such as cavities, broken teeth, swollen gums, tooth infections, and cleanings, that hadn't been addressed for years.

"Many of the volunteers had been up since 2:00 a.m. getting ready for the event, but no complaints were heard and everyone seemed happy to be there," stated Standage. "I was amazed at the community involvement in Brady, and to see the volunteers interacting and assisting patients with a kind, caring heart. So many came together for the greater good of those in need," said Johnson.

Whitley shared that this was a fulfilling experience. "I had the opportunity to talk with many individuals from different parts of Texas and from various backgrounds – a retired DPS officer, a retired veteran, a pregnant woman, and a waitress, just to name a few," said Whitley. "However, there was one elderly gentleman that I had a conversation with that just really touched my heart. He thanked me for volunteering my time and said that we were 'angels' there to help all the people that came. I told the gentleman that I was the one who was blessed, more than he would ever know."

Wesley Nurse Theresa Standage is working with her community for Texas Mission of Mercy's Kerrville event on March 25, 2017. To volunteer, please email tstandage@mhm.org. 

Contributing authors: Ann Scarth, Charlotte Johnson, Teresa Whitley and Theresa Standage.

How I fight compassion fatigue

By Pam Castles, MSN, MASF, RN, Wesley Nurse

When I started working as a Methodist Healthcare Ministries Wesley Nurse in October 2015, I had so many plans for my new ministry, and then God said, "Not so fast." I lost my mother in January and then my father in February. It has been a difficult start to a new job, to say the least, but I've had wonderful support from many team members. I have also been seeing my spiritual director more frequently which has provided the spiritual support that is so necessary when grieving.

My spiritual director and I have talked about many things that play a role in my physical, mental and spiritual health. We've talked about my role as a faith community nurse, the marginalization of the clients we see, and the stress we all experience in this role.

Providing care and compassion has both positive and negative impacts. To repeatedly hear stories about traumatic things happening to people opens our hearts in a way that we can relate to others with empathy, thus allowing us to better offer our knowledge and skills to improve their lives. However, we are also susceptible to trauma that is considered secondary in nature.

Compassion fatigue, the emotional strain that results when an individual hears about the firsthand trauma experiences of another, is frequently experienced by those in the caring professions. This secondary traumatization can result from working with patients who for example are experiencing homelessness, physical or emotional abuse, incarceration, and/or terminal illness. It is essential for caregivers to understand that even when you have not experienced loss or personal trauma, the act of caring for others who have puts you at risk for compassion fatigue.

In order to manage compassion fatigue, we must be able to identify the symptoms and causes. Some indicators of compassion fatigue include difficulty sleeping, feeling afraid, feeling a lost sense of self, emotional burnout, isolation, or feeling a reduced sense of personal accomplishment at work. Next, we must be willing to engage in professional and personal practices in which we do things differently. Self-care becomes more than a nice idea; it is an essential tool to perform our jobs as caregivers and compassionate healers. By better understanding the risks of compassion fatigue and how it impacts our professional and personal functioning, we have taken the first steps to experiencing the blessing and joy our work can provide.

Pam Castles, MSN, MASF, RN is a Wesley Nurse at Methodist Healthcare Ministries of South Texas, Inc. Methodist Healthcare Ministries' Wesley Nurse program is a faith-based, holistic health and wellness program committed to serving the least-served through education, health promotion and collaboration with individuals and communities to achieve improved wellness through self-empowerment. Learn more at www.mhm.org/programs/health-ministries. 

Why a localized approach matters

By Sandy Doughton, grant development manager

If your doctor only had one number they could choose from to best predict your health what would it be? Would it be your HbA1c level, cholesterol, weight, or complete blood count? What if we could rule out all medical tests, then what would this number be? As it turns out, your zip code number, or where you live, is the greatest predictor of how long you'll live.

A recent study published in the Journal of the American Medical Association analyzed income data and mortality rates for the U.S. population using federal income tax records and Social Security records for every individual from 1999 through 2014. The study titled "The Association Between Income and Life Expectancy in the United States" found that the richest American men live 15 years longer than the poorest men while the richest American women outlive the poorest women by 10 years.

Not only does the income gap play a role in longevity, but also this research lifts up the significant role that geography plays in predicting one's lifespan. The study revealed that people who live in poverty have even shorter lives in places that lack resources. For example, low-income Americans who live in San Francisco are predicted to live three years longer than someone with the same income in Detroit. Why? Comparing the two cities, San Francisco is far more environmentally friendly; it is surrounded by parks, less air pollution, strong smoking bans as well having more affluence and higher education than Detroit.

Where we live matters. Our zip code determines where we have access to opportunity structures: access to quality schools, role models, transportation, environmental quality, healthy foods and more. We know from the Social Determinants of Health, that 50 percent of what makes us healthy boils down to social and economic factors and the physical environment.

Many of the communities Methodist Healthcare Ministries serves in our 74-county service area, especially the rural areas, are under-resourced and shoulder significant health disparities. This same study found that Nueces County, home of Corpus Christi, has one of the lowest life expectancy outcomes for the poor. In Nueces County, the life expectancy for low-income residents is 76.6 years – nine years less than someone who is rich in the same county. Another way to put this in perspective, the New York Times called this gap in Nueces County "roughly equivalent to the difference in life expectancy between an average man in the United States and one in Somalia."

The role of geography is central to Methodist Healthcare Ministries' localized efforts. From health services, community engagement, philanthropic investments, spiritual connections and community education, this study amplifies the importance of place-based initiatives. For example, Methodist Healthcare Ministries is hard at work in the Coastal Bend region – building relationships, meeting with staff and partners, attending coalition meetings, and gathering information to better understand health care issues facing the community. Our team is listening for the differences and similarities across the region, from rural communities like Premont and Palacios to the urban area of Corpus Christi.

As we do this work, our team is learning more about existing collaborative efforts such as the First Thursday Community Meeting in Taft and the Homeless Issues Partnership in Corpus Christi. We are also exploring the potential of new collaborative opportunities. Let this study remind us all of the critical importance of closing the gap on health disparities in under-resourced areas. Through collaboration and the hard work of caring servants, together we can – and will – make our communities healthier.

Read more about the study in The New York Times article, "The Rich Live Longer Everywhere. For the Poor, Geography Matters." The article includes an interactive feature where you can explore the life expectancy in different counties throughout the U.S. 

Sandy Doughton is the Grant Development Manager for Methodist Healthcare Ministries' Community Engagement team. One of the team's projects is providing technical assistance to community partners in Methodist Healthcare Ministries' service regions, ranging from grant-writing, vetting grant opportunities, supporting collaborative funding initiatives and sharing information about development resources.

Case studies in diabetes management

By Anne N. Connor, director of community grants

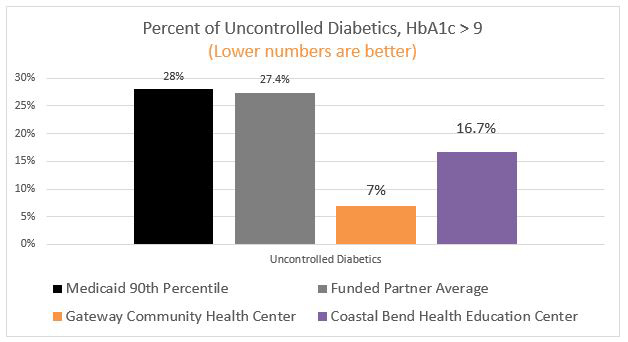
In 2015, two Methodist Healthcare Ministries funded partners, the Gateway Community Health Center in Laredo and the Texas A&M Health Science Center – Coastal Bend Health Education Center, did remarkably well at controlling HbA1c levels in diabetic patients.

The term HbA1c refers to glycated haemoglobin. It develops when haemoglobin, a protein within red blood cells that carries oxygen throughout your body, joins with glucose in the blood, becoming 'glycated.' By measuring glycated haemoglobin (HbA1c), clinicians are able to get an overall picture of what our average blood sugar levels have been over a period of weeks/months. For people with diabetes, this is important, since the higher the HbA1c the greater the risk of developing diabetes-related complications. 

Both partners did well at controlling HbA1c in their adult diabetic patients. The rate of uncontrolled HbA1c in Gateway patients was 7%, and the Coastal Bend Health Education Center had a rate of 16.7 %, both better than the Medicaid 90th percentile.

graph

When asked what made them successful, both organizations attributed it to the following components:

  Gateway Community Health Center: Leveraging long-term relationships Coastal Bend Health Education: Consistency and support
Integration Diabetes programs were integrated into medical practice. A multi-disciplinary diabetes education care team for diabetics included: a physician medical director, registered nurses, certified diabetes educator, registered dietitians and community health workers.
Supportive Intervention  Nutritional assessment and counseling: a 10-week diabetes self-management course included weekly outreach by phone to answer questions, and provided support and reminders. Bi-weekly support sessions provided group problem-solving and a buddy system.  A consistent patient-focused approach promoted lifestyle changes, diabetes self-management and social support. This included regular diabetes self-management education classes in English and Spanish, as well as monthly support groups and refresher trainings based on patient needs (i.e. glucometer training). Additionally, a three-part nutritional education course covered topics from food shopping to cooking to eating out.
Trusted Relationships  The community health workers that worked with patients and conducted the diabetes self-management courses had been with Gateway for over 10 years. This experience allowed staff to develop a rapport with patients and anticipate their needs. Community health workers were integrated into the community and facilitated patient access to support services. They followed up on patient progress and made home visits when the patients were identified as high risk with cultural and linguistic barriers. Community health workers enhanced the quality and cultural competence of program service delivery by serving as advocates.
Clinical Knowledge Careful, systematic monitoring of HbA1c at regular intervals helped move diabetics through different levels of support based on test results. All diabetic patients received a follow-up appointment every three months that monitored the progress of their treatment plan. Biometrics were obtained (HbA1c, blood pressure, random blood glucose, weight, BMI and percent of body fat) so patients could see changes in their health. This monitoring also allowed patients with urgent needs (such as a very high HbA1c) to be referred to medical providers for one-on-one crisis care.
Patient Convenience A one-stop shop model made it convenient for patients to access wrap-around services. Diabetic testing supplies were also provided year-round at low cost. Diabetes self-management education classes were offered in the day and in the evening at convenient locations around the region.
White close icon

Jaime Wesoloski

President & Chief Executive Officer

Jaime Wesolowski is the President and Chief Executive Officer at Methodist Healthcare Ministries. A healthcare executive with three decades of leadership experience, Jaime is responsible for the overall governance and direction of Methodist Healthcare Ministries. Jaime earned his Master’s Degree in Healthcare Administration from Xavier University, and his Bachelor’s of Science from Indiana University in Healthcare Administration. As a cancer survivor, Jaime is a staunch supporter of the American Cancer Society. He serves as Chair of the American Cancer Society’s South Texas Area board of directors and he was appointed as Chair to the recently created South Region Advisory Cabinet, covering eight states from Arizona through Alabama. Jaime believes his personal experience as a cancer survivor has given him more defined insight and compassion to the physical, emotional, and spiritual needs of patients and their families.